
Degenerative Disc Disease Treatment in Istanbul
How our medical team decides which disc level is generating your pain, what an intradiscal plan involves, and how to send your MRI from home.

Understanding Degenerative Disc Disease
Degenerative disc disease is not really a disease, and it is not simply the fact of a disc getting older. It is the pain and stiffness that arrive when an intervertebral disc loses water, loses height and stops sharing load the way it used to. Reports describe it in a vocabulary that alarms people more than it should: disc desiccation, loss of disc height, an annular tear or fissure, Modic changes in the bone above and below, a bulge or a protrusion at L4-L5 or L5-S1. The pain has a pattern of its own - worse sitting, worse leaning forward, worse after a long flight or a morning at a desk, easier walking or lying flat - and it sits low in the back, often spreading into the buttock or the back of the thigh. Most people arrive having been told the scan shows "wear and tear" and that nothing much can be done until a fusion becomes necessary.
The disc is the largest structure in the body with no blood supply of its own. Nutrition reaches the middle of it by diffusion, the environment inside is low in oxygen and acidic, and as the disc degenerates it fills with inflammatory signalling that irritates the nerve endings growing into the outer ring. That environment is exactly what an MSC treatment is aimed at in degenerative disc disease: the inflammatory signalling inside and around the disc, and the interaction between cells and the matrix that holds water and gives the disc its height. Our program works with mesenchymal stromal cells from Wharton's jelly, the gelatinous tissue inside a donated umbilical cord, and the source matters for a target this demanding - a young perinatal tissue rather than an adult one, cells that expand readily so a batch can be characterised and release-tested before it is used, a low-immunogenicity profile that is why this source is studied between unrelated people, and a strong secretory profile, because what these cells release is the entire point in a space where survival is hard. What is described is influence on that environment, not the restoration of a disc to the one you had at twenty.
Our medical team reads the MRI alongside how the pain actually behaves, because degenerative change appears on most adult spine scans and the level that looks worst is not reliably the level that hurts. We look at disc height and hydration, annular tears, Modic changes, facet involvement, foraminal narrowing and whether a nerve root is genuinely compressed, and we weigh the result of any diagnostic block or discography already performed. Progressive leg weakness, numbness in the saddle area or any change in bladder or bowel control means urgent assessment where you are, today, rather than a flight. Where a fusion has been recommended for instability, spondylolisthesis or stenosis with neurological signs, a spinal surgical opinion is the more useful conversation and our team will say so. Where an intradiscal plan is appropriate, it names the level, the side and the guidance used, and the aim may focus on sitting tolerance, the length of a drive or a flight, sleep and the first hour of the morning, scored before treatment and again at review. Send your spine MRI with the report and a short description of what makes the pain better and worse, and our medical team will tell you what it would target.
How Degenerative Disc Disease Can Affect Daily Life
Symptoms, severity and progression vary from person to person. Our medical team uses this kind of detail as context for your case review; it is not a diagnostic checklist. Diagnosis, and any change in your symptoms, belong with the clinician who knows your medical history.
- Low back pain that is worse sitting, bending forward or driving, and easier walking or lying flat
- Stiffness through the first part of the morning that takes time to loosen
- Flares after a long flight, a desk day or lifting, lasting days rather than hours
- Aching or radiating pain into the buttock or the back of the thigh
- Broken sleep and a shrinking tolerance for staying in any one position
Which level is actually hurting
Most lumbar MRIs show disc changes, and only some of those changes explain the pain. This visual connects what the discs look like with the level our medical team is trying to identify.
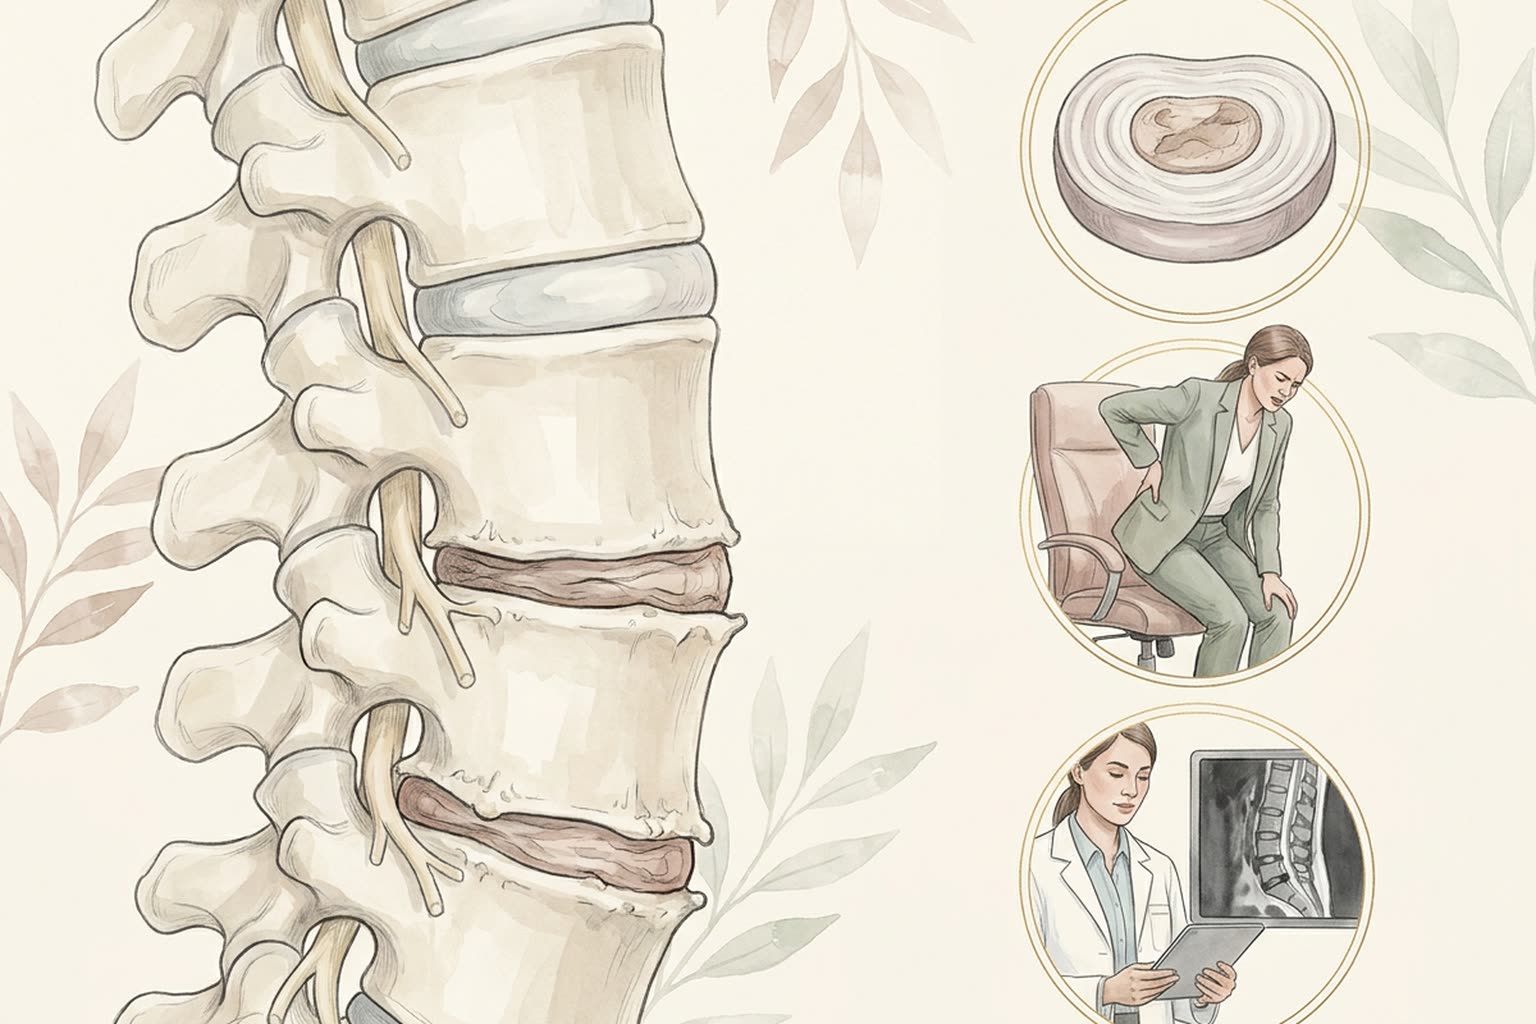
Clinical context

Microscopic research viewIllustrative detail
- Height, hydration, and the rings
- A disc loses water before it loses height, and the outer rings of the annulus carry the nerve endings that matter for pain.
- Imaging and symptoms together
- Disc changes are common on MRI at every age, so the findings are read against where your pain actually is and what provokes it.
- Everyday measures
- Sitting tolerance, rising from a chair, driving distance, sleep position and morning stiffness make change easier to read.
Why Regenerative Medicine Is Being Studied in Disc Disease
These are the biological mechanisms researchers are investigating. A mechanism is a reason to study a treatment, not a promise of benefit for an individual patient. Our medical team will explain how much of this research applies to your own diagnosis.
- The target in a degenerating disc is its environment: inflammatory signalling inside the nucleus and the outer ring, and interaction with the matrix that holds water and gives the disc its height
- The disc has no blood supply of its own and is low in oxygen and acidic, so the cell source, the dose and the volume placed inside it are planned rather than assumed
- Intradiscal delivery is performed under fluoroscopic guidance, with the level and the side named in your written plan
- A disc, a facet joint and a nerve root are different targets with different reasoning, and one plan does not stand in for another
- Influencing that environment is not the same as restoring lost disc height or undoing degeneration on a scan, and the two are never merged into one sentence
- The aim may focus on sitting tolerance, driving and flying, sleep and the first hour of the morning, scored before treatment and at set intervals
Research maturity
What the Research Currently Shows for Disc Disease
How far published research has travelled for each approach, from laboratory work through to established standard care. It describes the maturity of the evidence, not how well any option works and not what to expect in an individual case.
- 01Laboratory and animal work
- 02Early human studies
- 03Controlled trials under way
- 04Established standard of care
Core rehabilitation, pain management and selective surgical decompression or fusion
Standard conservative and surgical spine care guided by neurological examination and concordant MRI findings.
Established standard of care
Intradiscal mesenchymal progenitor or stromal cell injection
Randomised controlled studies have evaluated pain and functional scores in single-level disc degeneration, though durable disc height restoration remains uncertain.
Controlled trials under way
The proposed mechanism, illustrated
What is being studied in the disc in Disc Disease

Your case review
How Our Medical Team Reviews Your Case
Your review starts with the confirmed diagnosis, recent reports and imaging, current treatment, medical history, and the outcome that matters most to you. Not everyone is suitable for regenerative medicine, and our team will say so when the care you already receive is the better route.
- A recent lumbar or cervical MRI with the radiology report, for our medical team to read against your symptoms
- The levels named, with disc height, hydration, annular tears and Modic changes as described on the report
- A clear account of what makes the pain better and worse across an ordinary day, since a disc pattern and a facet pattern differ
- Results of any diagnostic block or discography, and the response to previous epidural or facet injections
- No warning signs needing urgent local assessment: progressive weakness, saddle numbness, or bladder and bowel change
- A spinal surgical opinion where instability, spondylolisthesis or stenosis with neurological signs points towards decompression or fusion
How Treatment for Disc Disease Is Planned at Our Istanbul Clinic
The path international patients follow with us, from the first review of your records to follow-up after you return home. The exact steps depend on what your medical review finds.
Send your medical records
Recent reports, imaging, your current medication, and what you hope treatment will help with. It lets our medical team make the review specific to you.
Start your case reviewSend your medical records
Your case review starts with the confirmed diagnosis, recent reports and imaging, current medications, previous procedures and the outcomes that matter most to you. Everything can be sent digitally from home, long before travel is discussed.
Case review by our medical team
Our medical team reads the file against your diagnosis, disease stage, imaging, laboratory results, current treatment and any contraindications, then decides whether regenerative medicine is appropriate for you and which goals are realistic to discuss.
Your written treatment plan
When treatment is appropriate, you receive the plan in writing: the cell material and how it is prepared, the dose, the route of administration, the number of sessions, the monitoring involved and an itemized cost with no assumed extras.
Your treatment in Istanbul
On arrival our team repeats the checks that matter for your case, confirms the plan with you, and carries out treatment under medical supervision with an observation period afterwards. Your coordinator handles scheduling, timings and what each day involves.
Follow-up and monitoring
Before you fly home we agree what will be measured, when it will be reviewed and how to reach us. Follow-up continues remotely and can be shared with your own doctors, so your treatment plan and your local care stay aligned.
Your treatment plan
What Our Medical Team Explains Before You Decide
"Stem cells" and "exosomes" name a category, not a specific product. What matters in your plan is the source of the material, how it was prepared, the route and the dose, the clinical setting, and why you were considered suitable. Our medical team sets each of those out for the treatment being proposed to you.
We plan treatment alongside the care you already receive, so keep your own clinician involved and record a clear baseline before you travel. For the practical side, read the Istanbul treatment trip guide and the cost guide, then ask us for an itemized estimate.
- Which published research applies to your diagnosis and to the route we propose.
- Where the biological material comes from, how it is prepared, and how it is documented.
- The possible side effects and the contraindications that apply to your procedure.
- Which functional outcome is measured before treatment and again at follow-up.
- How treatment sits alongside your existing care, including the option of not treating.
- Who to contact about follow-up, or about a complication, once you are home.
- What your estimate includes and excludes, and what is due before you travel.
Next step
Start with a medical case review
Send your diagnosis, recent reports, imaging and current medication, and tell us what you want treatment to help with.
Degenerative Disc Disease: Questions Patients Ask Us
What does degenerative disc disease treatment cost in Turkey?
The quote is built level by level rather than sold as a package: the imaging review, the number of discs treated, fluoroscopic guidance, sedation, any diagnostic block performed first and the monitoring afterwards each appear on their own line. Our patient coordination team sends it in writing, including what applies to the cost if a block does not confirm the level, before you book flights.
Can this rebuild a disc that has lost its height?
Restoring the height of a collapsed disc is not what this research describes, and our medical team will not tell you otherwise. The target is the environment inside and around the disc, particularly the inflammatory signalling that irritates the nerve endings in its outer ring. The goals we write down are about sitting, driving, sleeping and what you can do through a working day, measured with the same scores before treatment and at review.
Is this an alternative to spinal fusion?
They answer different questions. A fusion is an operation for instability, slippage or nerve compression that has stopped responding to anything else, and it has decades of surgical experience behind it. An intradiscal plan is directed at the environment inside a disc that is still doing its job badly rather than not at all. Where your imaging and your neurological examination point to surgery, our medical team points you to a spinal surgeon.
How long do I need to stay in Istanbul for an intradiscal procedure?
Your plan sets it out before you book: the assessment, the procedure day, the observation afterwards, the restrictions on lifting, sitting and flying for the following days, and when our team is comfortable with you travelling. An intradiscal procedure is planned with more caution than a joint injection, so the stay is built around the recovery rather than around the flights.
Are Wharton's jelly stem cells used to treat Degenerative Disc Disease in Istanbul?
Yes. Our regenerative medicine program works with mesenchymal stromal cells (MSCs) grown from Wharton's jelly, the gelatinous tissue inside the umbilical cord. It is donated after a healthy birth with written maternal consent, from tissue that would otherwise be discarded, so nothing is taken from mother or baby and none of the ethical questions attached to embryonic sources arise. Because these cells expand readily in culture, a batch is characterised and release-tested before it reaches anyone. Your written plan names the material, how it is prepared, the dose, the route of administration and the schedule, and our medical team explains why each of those was chosen for your case.
Why use donor cells from Wharton's jelly rather than my own cells for Degenerative Disc Disease?
Wharton's jelly is a young, perinatal tissue rather than an adult one, so the starting material does not carry the age or the health history of the person being treated, and nothing has to be harvested from you on the day. These cells also have a low-immunogenicity profile, which is why this source is studied for use between unrelated people. Most of all, they are strong secretors: the signalling molecules MSCs release are the mechanism most current research centres on, and that is what a plan is built around.
How long do international patients stay in Istanbul for Degenerative Disc Disease treatment?
The length of stay follows your plan: the route of administration, the number of sessions, the monitoring after each one, and any mobility or assistance you need. Our patient coordination team confirms appointment dates, daily timings and the expected length of the visit in writing before you book flights.
Is stem cell therapy for Degenerative Disc Disease safe?
No medical procedure is free of risk. Our medical team screens for infection, bleeding risk, medication interactions and other contraindications before treatment, explains the risks specific to the route used in your plan, and monitors you during administration and afterwards. If something makes treatment unsafe for you, we say so instead of proceeding.
What can stem cell therapy realistically aim for in Degenerative Disc Disease?
Goals are set with you and described as aims, not results. Regenerative medicine treatments are planned individually, responses vary between patients and no clinical outcome can be guaranteed. Your plan states what will be measured, when it will be reviewed, and how treatment sits alongside the care you already receive.
How do I start a Degenerative Disc Disease case review from outside Turkey?
Send your confirmed diagnosis, recent reports and imaging, your current medication list, previous procedures and the goals that matter to you. Our medical team reviews them remotely and comes back with an assessment of whether treatment in Istanbul is appropriate for your case, and what the next step would be.
Medical Disclaimer: Information on this page is educational and is not personal medical advice. Regenerative medicine treatments are planned individually, responses vary and no clinical outcome can be guaranteed. Some of the approaches described remain investigational. Suitability is confirmed only after medical review, and treatment is planned alongside your existing care.

Evening on the Bosphorus, with a ferry and the bridge beyond. It shows the city you would travel to, not our clinic, your accommodation, or a service included in a plan.
Plan for movement and access with Disc Disease
We go through walking limits, stairs, vehicle transfers, mobility aids, companion support, and a realistic return journey before an Istanbul visit is booked.
Keep researching
Treatments and Related Conditions for Degenerative Disc Disease
Treatment
Targeted Injection Therapy
Image-guided injection into a specific joint or tissue, and the cases where our team proposes it.
Learn more→
Treatment
Stem Cell Therapy
Our MSC-based treatment in Istanbul: the cells we use, how a plan is built, and what treatment involves.
Learn more→
Treatment
Exosome Therapy
Vesicle-based preparations, how they differ from a cell therapy, and where the research currently stands.
Learn more→
Treatment
Intravenous Stem Cell Therapy
How an infusion session runs, how you are monitored, and when our team proposes this route.
Learn more→
Condition
Back Pain
How regenerative medicine is planned for Back Pain at our Istanbul clinic.
Learn more→
Condition
Spinal Arthritis
How regenerative medicine is planned for Spinal Arthritis at our Istanbul clinic.
Learn more→
Condition
Avascular Necrosis (AVN)
How regenerative medicine is planned for Avascular Necrosis (AVN) at our Istanbul clinic.
Learn more→
Condition
Osteoarthritis
How regenerative medicine is planned for Osteoarthritis at our Istanbul clinic.
Learn more→
Condition
Neuropathy
How regenerative medicine is planned for Neuropathy at our Istanbul clinic.
Learn more→
More from our clinic
Planning treatment for Disc Disease in Istanbul
The practical side of treatment at our clinic: what the research shows, who may be suitable, what a plan costs, and how your stay in Istanbul and your follow-up are arranged.
Cost, Outcomes & Istanbul
- Visit our Istanbul clinicWhere we are, how patients reach us, and what to arrange before you travel.
- Understand treatment pricingWhat shapes a quote, and what an itemized estimate from our clinic covers.
- Planning your Istanbul treatment tripRecords, travel timing, local transport, accommodation, and follow-up after you fly home.
- Choosing a stem cell clinic in IstanbulHow we document candidacy, pricing, clinical oversight, and aftercare for international patients.
- Rules and oversight in TurkeyHow regenerative medicine is regulated in Türkiye, and the paperwork that accompanies treatment.
- Reading stem cell success ratesWhat a published percentage can and cannot tell you about your own diagnosis.
- What your treatment quote includesWhat the clinical fee covers, which items are listed separately, and what moves the total.
- What to expect during treatmentThe remote case review, your written plan, the treatment day, and follow-up once you are home.
- Longevity and healthy-ageing care in IstanbulWhat our longevity programme assesses, and how it differs from treating a diagnosed condition.
- What exosome treatment in Istanbul costsHow we structure an exosome quote, and the line items a written estimate names.
- Exosome therapy questions we are askedSourcing, dosing, regulation, and the documentation that accompanies a proposed treatment.
- Medical travel to Turkey: patient guideHow remote record reviews, clinic scheduling, and travel logistics fit together.
- Comparing treatment abroad: Turkey vs MexicoQuestions to ask when comparing clinics, cell documentation, and oversight across countries.
Condition guides
Treatments & the science
- Stem Cell Therapy Overview
- Introduction to Stem Cell Therapy
- Umbilical Cord Stem Cells (UC-MSCs)
- Mesenchymal Stem Cell (MSC) Therapy
- How Stem Cells Work
- Safety & Treatment Process
- Exosome Therapy Overview
- How Exosomes Work
- Stem Cells vs Exosomes
- Intravenous (IV) Stem Cell Therapy
- Intrathecal Stem Cell Therapy
- Longevity Program
- See all treatments →
International patient support
Ask our medical team about treatment for Degenerative Disc Disease.
Send your diagnosis, recent reports, imaging and current medication. Our medical team reviews them and explains which regenerative medicine options may fit your case, and what treatment in Istanbul would involve.
Nothing needs to be booked to begin. Our patient coordination team plans your visit to Istanbul once your treatment plan is agreed.